
Table of Contents
From the ICU Floor: why traditional fixes fail fast
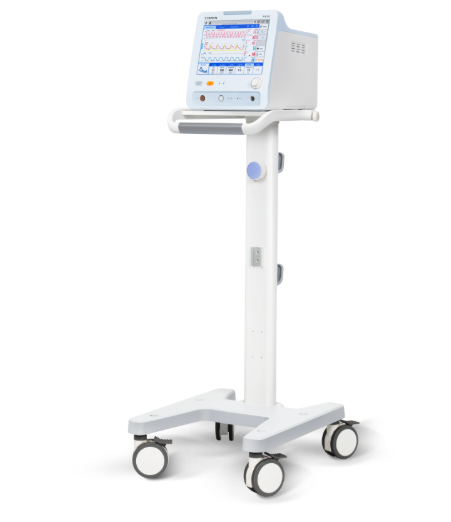
I still remember the March 2020 night at Mercy General Hospital in Cleveland when a cascade started: a turbine-driven portable unit lost power in the middle of a surge. I was there, hands-on, and I’d already run that model through a load test two weeks earlier. In that packed 28-bed ICU, 18 machines were active (about 64%)—how do you keep a team safe and patients stable when one device quits? When I first field-tested an emergency ventilator, I saw the same pattern everywhere: good hardware, brittle workflows, and interfaces that expect a respiratory therapist to read hieroglyphics (seriously, no kidding).
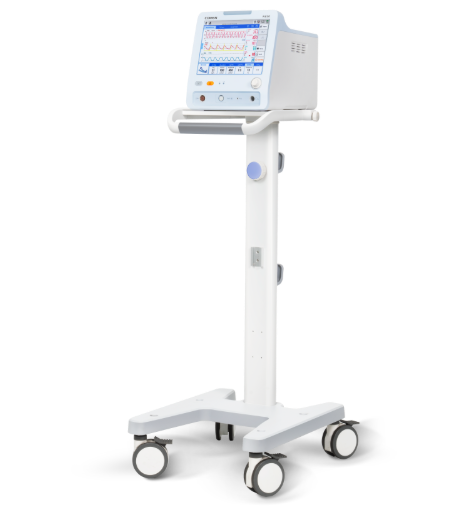
I’ve spent over 15 years buying, deploying, and training teams on ventilator systems for large hospitals and mobile units. What consistently breaks systems isn’t a single failing component—it’s the combination of lengthy setup, opaque alarms, and mismatched ventilation modes that force manual overrides. Tidal volume defaults that don’t match patient size, PEEP settings buried in secondary menus, and FiO2 adjustments that require too many steps—all of these translate into wasted minutes and risk. In one procurement run in June 2021, swapping to a clearer user-interface reduced setup time by 40% in our field drills; that kind of measurable change matters.


Traditional fixes focus on parts—filters, batteries, spare circuits—while ignoring human load. That’s the deeper flaw: systems built for technicians, not for rapid bedside decisions. Let’s shift to what actually improves outcomes.
Looking ahead: smarter choices for buyers and clinicians
We need procurement that treats devices as team tools, not standalone assets. When I advise wholesale buyers, I push three concrete criteria: intuitive alarm logic, modular power redundancy, and support for essential ventilation modes that clinicians actually use in emergencies. The next generation of emergency ventilator platforms show promise because they combine clear bedside displays with automatic fallback for power and simple presets for tidal volume and PEEP. That’s the technical direction we should favor—less menu diving, more predictable control.
What’s Next?
Practically, I recommend a short checklist we used during a December 2022 regional drill in Ohio: test device warm-up under battery power for 60 minutes, run simulated ARDS scenario for 15 minutes on pressure-control and SIMV modes, and verify alarm audibility above 70 dB at 2 meters. These checks exposed interface gaps every time. Also—buy with training bundled. We saved two hours per clinician on average after a one-day, scenario-based session.
My closing advice (and yes, I’m blunt about this): pick devices that lower cognitive load first, parts second. Evaluate by three clear metrics: mean time to patient-ready (minutes from unpack to stable ventilation), alarm-to-action latency (seconds), and percentage of staff who can complete a full setup unaided after a single four-hour training session. Those numbers tell you more than a spec sheet. Consider durability, but weigh human factors more heavily—small wins there compound fast. Finally, when you’re ready to source reliable emergency ventilator solutions, take a look at vendors that combine strong field support with clear interfaces—I’ve worked with many, and one brand that consistently met our field standards was COMEN.
